<?xml version="1.0" encoding="utf-8"?><feed xmlns="http://www.w3.org/2005/Atom" ><generator uri="https://jekyllrb.com/" version="4.4.1">Jekyll</generator><link href="http://anthonycox.org/feed.xml" rel="self" type="application/atom+xml" /><link href="http://anthonycox.org/" rel="alternate" type="text/html" /><updated>2026-09-07T08:28:13+01:00</updated><id>http://anthonycox.org/feed.xml</id><title type="html">Anthony Cox</title><subtitle>This is the webpage and blog of Anthony R Cox, which is mainly concerned
 with issues around drug safety, pharmacovigilance, and the use of medicines.</subtitle><entry><title type="html">Principles and Practice of Pharmacovigilance and Drug Safety</title><link href="http://anthonycox.org/pharmacovigilance/2024/08/28/drugsafety.html" rel="alternate" type="text/html" title="Principles and Practice of Pharmacovigilance and Drug Safety" /><published>2024-08-28T09:00:00+01:00</published><updated>2024-08-28T09:00:00+01:00</updated><id>http://anthonycox.org/pharmacovigilance/2024/08/28/drugsafety</id><content type="html" xml:base="http://anthonycox.org/pharmacovigilance/2024/08/28/drugsafety.html"><![CDATA[<p><img src="/assets/principlesofdrugsafety.png" alt="Principles and Practice of Pharmacovigilance and Drug Safety" /></p>

<p>I am pleased to annouce the publication of a new textbook <a href="https://link.springer.com/book/10.1007/978-3-031-51089-2">‘Principles and Practice of Pharmacovigilance and Drug Safety’</a>. It is an edited volume with over 50 expert authors with an international reach, with each chapter peer-reviewed.</p>

<blockquote>
  <p>The science of drug safety and pharmacovigilance has rapidly evolved in the 21st century. The knowledge and principles it contains are of increasing importance in clinical and practice settings. The aim of this book is to deal with the gap in knowledge about pharmacovigilance and drug safety, including the application of pharmacovigilance knowledge to individual patient cases in clinical practice.</p>

  <p>A holistic approach is taken with each chapter written from the perspective of a practitioner, industry personnel, researcher, or regulator, creating a synergy between drug safety, pharmacovigilance, and clinical practice. Chapters offer key material on adverse drug reactions, medication errors, prescribing safety, pharmacovigilance as well as data sources used in drug safety and pharmacovigilance. Each chapter is structured as a self-contained learning resource, with learning objectives, and worked cases.</p>

  <p>The book is suitable for undergraduate healthcare professions, postgraduate students, researchers, clinical practitioners – including those with prescribing responsibilities. It will also be useful for professionals moving from a clinical practice role to a specialist pharmacovigilance role. For those already in a pharmacovigilance role, the book offers insight into the theory and practice of drug safety and pharmacovigilance in clinical settings.</p>
</blockquote>

<p>The seed of this project was planted 4 years ago, when in the midst of the pandemic in August 2020, <a href="https://scholar.google.com/citations?user=cfuVS3cAAAAJ&amp;hl=en">Jimmy Jose</a> contacted me with his ideas about creating a new textbook in the area of pharmacovigilance. We both had similar views on trying to create something that straddled the regulatory, scientific, and clinical practice. Co-ordinating such an endeavour was a massive under-taking, and we were grateful to have a third editor join us, <a href="https://scholar.google.co.uk/citations?user=hjzol9gAAAAJ&amp;hl=en">Vibhu Paudyal</a>. I hope we have succeeded in creating what we intended, and I thank the international authors for their hard work.</p>

<p>The two chapters I contributed to are:</p>

<blockquote>
  <p>van Hunsel, F., Younus, M.M., Cox, A.R. (2024). Patient and Public Involvement in Pharmacovigilance. In: Jose, J., Cox, A.R., Paudyal, V. (eds) Principles and Practice of Pharmacovigilance and Drug Safety. Springer, Cham. <a href="https://link.springer.com/chapter/10.1007/978-3-031-51089-2_12">https://doi.org/10.1007/978-3-031-51089-2_12</a></p>
</blockquote>

<blockquote>
  <p>Jose, J., Cox, A.R., Bate, A. (2024). Introduction to Drug Safety and Pharmacovigilance. In: Jose, J., Cox, A.R., Paudyal, V. (eds) Principles and Practice of Pharmacovigilance and Drug Safety. Springer, Cham. <a href="https://link.springer.com/chapter/10.1007/978-3-031-51089-2_1">https://doi.org/10.1007/978-3-031-51089-2_1</a></p>
</blockquote>]]></content><author><name></name></author><category term="pharmacovigilance" /><summary type="html"><![CDATA[I am pleased to annouce the publication of a new textbook ‘Principles and Practice of Pharmacovigilance and Drug Safety’. It is an edited volume with over 50 expert authors with an international reach, with each chapter peer-reviewed. The science of drug safety and pharmacovigilance has rapidly evolved in the 21st century. The knowledge and principles it contains are of increasing importance in clinical and practice settings. The aim of this book is to deal with the gap in knowledge about pharmacovigilance and drug safety, including the application of pharmacovigilance knowledge to individual patient cases in clinical practice. A holistic approach is taken with each chapter written from the perspective of a practitioner, industry personnel, researcher, or regulator, creating a synergy between drug safety, pharmacovigilance, and clinical practice. Chapters offer key material on adverse drug reactions, medication errors, prescribing safety, pharmacovigilance as well as data sources used in drug safety and pharmacovigilance. Each chapter is structured as a self-contained learning resource, with learning objectives, and worked cases. The book is suitable for undergraduate healthcare professions, postgraduate students, researchers, clinical practitioners – including those with prescribing responsibilities. It will also be useful for professionals moving from a clinical practice role to a specialist pharmacovigilance role. For those already in a pharmacovigilance role, the book offers insight into the theory and practice of drug safety and pharmacovigilance in clinical settings. The seed of this project was planted 4 years ago, when in the midst of the pandemic in August 2020, Jimmy Jose contacted me with his ideas about creating a new textbook in the area of pharmacovigilance. We both had similar views on trying to create something that straddled the regulatory, scientific, and clinical practice. Co-ordinating such an endeavour was a massive under-taking, and we were grateful to have a third editor join us, Vibhu Paudyal. I hope we have succeeded in creating what we intended, and I thank the international authors for their hard work. The two chapters I contributed to are: van Hunsel, F., Younus, M.M., Cox, A.R. (2024). Patient and Public Involvement in Pharmacovigilance. In: Jose, J., Cox, A.R., Paudyal, V. (eds) Principles and Practice of Pharmacovigilance and Drug Safety. Springer, Cham. https://doi.org/10.1007/978-3-031-51089-2_12 Jose, J., Cox, A.R., Bate, A. (2024). Introduction to Drug Safety and Pharmacovigilance. In: Jose, J., Cox, A.R., Paudyal, V. (eds) Principles and Practice of Pharmacovigilance and Drug Safety. Springer, Cham. https://doi.org/10.1007/978-3-031-51089-2_1]]></summary></entry><entry><title type="html">Vaccine boost</title><link href="http://anthonycox.org/vaccines/2021/12/03/accelerating-boosters.html" rel="alternate" type="text/html" title="Vaccine boost" /><published>2021-12-03T17:00:00+00:00</published><updated>2021-12-03T17:00:00+00:00</updated><id>http://anthonycox.org/vaccines/2021/12/03/accelerating-boosters</id><content type="html" xml:base="http://anthonycox.org/vaccines/2021/12/03/accelerating-boosters.html"><![CDATA[<p><img src="/assets/spike.jpg" alt="SARS-CoV-2" /></p>

<p>Yet again, a new phase of the pandemic in the UK. First there was the prodrome of general awareness of a new virus in China, with the uncertainties, and false re-assurances, evaporating away to leave the reality of the first wave. Deaths. Lockdowns. New uncertainties. How does it spread? Should I wash my shopping? Should we wear masks? The answer to the latter I found was no — I was refused access to a blood donation centre because I declined to take my mask off.</p>

<p>Cases fell, and second phase arrived. A summer of ‘eat out, help out’ commenced, when you could nervously try the new normal. I watched Tenet in two masks — they were required in the newly opened cinemas. I ate breakfast in a hotel with ineffective plastic screens between tables. It felt like the eye of a storm passing, and, to some, the storm receding. It hadn’t.</p>

<p>Phase 3. A gradual worsening, some due to our prior help at eating out, the arrival of Delta, and the shaft of light of vaccines. A battle between vaccination and the virus, with many deaths. A cold, dark lockdown. Then a summer of confidence courtesy of science. The fourth phase has been an uneasy accommodation with SARS-COV-2, with high cases, and lower deaths. The virus is not yet endemic, but arguments are. Worse case predictions, post freedom day, were thankfully wrong.</p>

<p>Now we have the fifth phase. A new variant (Omicron) has arrived, sufficiently different to Delta to raise concerns about possible reduced effectiveness of the vaccines, with <a href="https://twitter.com/mugecevik/status/1466845357686640640?s=20">a potentially far higher level of transmission</a>. Cases in South Africa have rapidly increased, and UK cases appear to be rising (<a href="https://www.gov.uk/government/news/covid-19-variants-identified-in-the-uk">134 today</a>). There is not enough data to make any strong claims about whether it is mild or severe.</p>

<p>This time it is a race between boosters and a possible Omicron wave of unknown potential to cause harm. The UK target is to give 25 million doses before the end of January, to raise the wall of vaccine-induced immunity to minimise the potential harms from this round of uncertainties. Liz Breen and I have an article assessing if this target can be met at <a href="https://theconversation.com/omicron-britain-plans-to-vaccinate-25-million-in-two-months-but-can-it-be-done-173002">The Conversation</a>. We are optimistic on that front.</p>

<blockquote>
  <p>The key ingredients for a successful booster programme have thus been promised – vaccine stock, vaccination sites and staff resources. If they can be made available in a timely fashion, then replicating the vaccination drive of the first half of 2021 is possible – as is meeting the government’s January target. Encouragingly, vaccination rates were already improving before these changes</p>
</blockquote>

<p>Everything else is up in the air, and the gradual clarity on Omicron over the next few weeks will tell us whether this phase is an easy or a hard one. Until then, this comment from a <a href="https://www.bloomberg.com/news/articles/2021-12-03/omicron-up-close-south-africa-s-experts-tell-their-stories">Bloomberg article</a> — that has been shared widely as evidence Omicron is mild — is probably a good default position to hold.</p>

<blockquote>
  <p>“The only ones putting their hand on their hearts and telling the world don’t worry, this is going to be mild, haven’t learned enough humility yet in the face of this virus.”</p>
</blockquote>

<p>Photo from <a href="https://unsplash.com/photos/rnr8D3FNUNY">Fusion Medical Animation</a></p>]]></content><author><name></name></author><category term="vaccines" /><summary type="html"><![CDATA[Yet again, a new phase of the pandemic in the UK. First there was the prodrome of general awareness of a new virus in China, with the uncertainties, and false re-assurances, evaporating away to leave the reality of the first wave. Deaths. Lockdowns. New uncertainties. How does it spread? Should I wash my shopping? Should we wear masks? The answer to the latter I found was no — I was refused access to a blood donation centre because I declined to take my mask off. Cases fell, and second phase arrived. A summer of ‘eat out, help out’ commenced, when you could nervously try the new normal. I watched Tenet in two masks — they were required in the newly opened cinemas. I ate breakfast in a hotel with ineffective plastic screens between tables. It felt like the eye of a storm passing, and, to some, the storm receding. It hadn’t. Phase 3. A gradual worsening, some due to our prior help at eating out, the arrival of Delta, and the shaft of light of vaccines. A battle between vaccination and the virus, with many deaths. A cold, dark lockdown. Then a summer of confidence courtesy of science. The fourth phase has been an uneasy accommodation with SARS-COV-2, with high cases, and lower deaths. The virus is not yet endemic, but arguments are. Worse case predictions, post freedom day, were thankfully wrong. Now we have the fifth phase. A new variant (Omicron) has arrived, sufficiently different to Delta to raise concerns about possible reduced effectiveness of the vaccines, with a potentially far higher level of transmission. Cases in South Africa have rapidly increased, and UK cases appear to be rising (134 today). There is not enough data to make any strong claims about whether it is mild or severe. This time it is a race between boosters and a possible Omicron wave of unknown potential to cause harm. The UK target is to give 25 million doses before the end of January, to raise the wall of vaccine-induced immunity to minimise the potential harms from this round of uncertainties. Liz Breen and I have an article assessing if this target can be met at The Conversation. We are optimistic on that front. The key ingredients for a successful booster programme have thus been promised – vaccine stock, vaccination sites and staff resources. If they can be made available in a timely fashion, then replicating the vaccination drive of the first half of 2021 is possible – as is meeting the government’s January target. Encouragingly, vaccination rates were already improving before these changes Everything else is up in the air, and the gradual clarity on Omicron over the next few weeks will tell us whether this phase is an easy or a hard one. Until then, this comment from a Bloomberg article — that has been shared widely as evidence Omicron is mild — is probably a good default position to hold. “The only ones putting their hand on their hearts and telling the world don’t worry, this is going to be mild, haven’t learned enough humility yet in the face of this virus.” Photo from Fusion Medical Animation]]></summary></entry><entry><title type="html">Talking about vaccines</title><link href="http://anthonycox.org/vaccines/2021/11/07/vaccinesafetypodcast.html" rel="alternate" type="text/html" title="Talking about vaccines" /><published>2021-11-07T07:00:00+00:00</published><updated>2021-11-07T07:00:00+00:00</updated><id>http://anthonycox.org/vaccines/2021/11/07/vaccinesafetypodcast</id><content type="html" xml:base="http://anthonycox.org/vaccines/2021/11/07/vaccinesafetypodcast.html"><![CDATA[<p><img src="/assets/cdcvaccine.jpg" alt="Influenzavaccine" /></p>

<p>I recently appeared on the Uppsala Monitoring Centre podcast <em>Drug Safety Matters</em> on the subject of talking about <a href="https://www.buzzsprout.com/618871/9482726">vaccine safety</a>.</p>

<blockquote>
  <p>With vaccine hesitancy on the rise and misinformation spreading like wildfire on social media, drug safety specialists may have a hard time knowing how to talk about side effects without affecting people’s trust in vaccinations. Anthony Cox from the University of Birmingham and Daniel Salmon from the Institute for Vaccine Safety share their best advice for balanced and responsible vaccine safety communication.</p>
</blockquote>

<blockquote>

  <p><strong>Tune in to find out:</strong></p>
</blockquote>

<blockquote>

  <ul>
    <li>Why we can’t allow bad actors to damage the drive for openness in research and data</li>
    <li>Why we should be open about uncertainty and always frame risks in the context of benefits</li>
    <li>How to prevent public health advocacy from biasing the science of vaccine safety</li>
  </ul>
</blockquote>

<p>Photo from <a href="https://unsplash.com/photos/GZkhG_EvWfY">CDC</a></p>]]></content><author><name></name></author><category term="vaccines" /><summary type="html"><![CDATA[I recently appeared on the Uppsala Monitoring Centre podcast Drug Safety Matters on the subject of talking about vaccine safety. With vaccine hesitancy on the rise and misinformation spreading like wildfire on social media, drug safety specialists may have a hard time knowing how to talk about side effects without affecting people’s trust in vaccinations. Anthony Cox from the University of Birmingham and Daniel Salmon from the Institute for Vaccine Safety share their best advice for balanced and responsible vaccine safety communication. Tune in to find out: Why we can’t allow bad actors to damage the drive for openness in research and data Why we should be open about uncertainty and always frame risks in the context of benefits How to prevent public health advocacy from biasing the science of vaccine safety Photo from CDC]]></summary></entry><entry><title type="html">Communicating Vaccine Safety</title><link href="http://anthonycox.org/drug_safety/2021/10/23/vaccinesafety.html" rel="alternate" type="text/html" title="Communicating Vaccine Safety" /><published>2021-10-23T08:00:00+01:00</published><updated>2021-10-23T08:00:00+01:00</updated><id>http://anthonycox.org/drug_safety/2021/10/23/vaccinesafety</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2021/10/23/vaccinesafety.html"><![CDATA[<p><img src="/assets/vaccine.jpeg" alt="AstraZenecaZaccine" /></p>

<p>Just a short post linking to an article about communicating vaccine safety, which I contributed to, at <a href="https://uppsalareports.org/articles/talking-about-vaccine-safety/">Uppsala Reports</a>. Here is an excerpt.</p>

<blockquote>
  <p>We can’t allow bad actors to damage the drive for openness in research and data,” Cox says. Science is about finding the closest approximation to the truth, he explains, and it is essential that we have open discussions about what that is. Trying to control, hide, or bias the truth will only generate distrust in authorities.</p>
</blockquote>

<blockquote>
  <p>Dr Daniel Salmon, director of the Institute for Vaccine Safety at Johns Hopkins School of Public Health in the US, agrees that the risks and benefits of vaccines must be discussed with honesty and objectivity.</p>
</blockquote>

<blockquote>
  <p>“Vaccines are such an impactful medical and public health intervention, and we have to be careful not to fall into the trap of overselling their value or underselling their risks,” he explains. “If we overstate the benefits, we run the risk of losing people’s trust in the science and system.”</p>
</blockquote>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[Just a short post linking to an article about communicating vaccine safety, which I contributed to, at Uppsala Reports. Here is an excerpt. We can’t allow bad actors to damage the drive for openness in research and data,” Cox says. Science is about finding the closest approximation to the truth, he explains, and it is essential that we have open discussions about what that is. Trying to control, hide, or bias the truth will only generate distrust in authorities. Dr Daniel Salmon, director of the Institute for Vaccine Safety at Johns Hopkins School of Public Health in the US, agrees that the risks and benefits of vaccines must be discussed with honesty and objectivity. “Vaccines are such an impactful medical and public health intervention, and we have to be careful not to fall into the trap of overselling their value or underselling their risks,” he explains. “If we overstate the benefits, we run the risk of losing people’s trust in the science and system.”]]></summary></entry><entry><title type="html">Blood clot fears: how misapplication of the precautionary principle may undermine public trust in vaccines.</title><link href="http://anthonycox.org/drug_safety/2021/03/16/precautionaryprinciple.html" rel="alternate" type="text/html" title="Blood clot fears: how misapplication of the precautionary principle may undermine public trust in vaccines." /><published>2021-03-16T07:00:00+00:00</published><updated>2021-03-16T07:00:00+00:00</updated><id>http://anthonycox.org/drug_safety/2021/03/16/precautionaryprinciple</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2021/03/16/precautionaryprinciple.html"><![CDATA[<p><img src="/assets/astrazeneca.jpeg" alt="AstraZenecaZaccine" /></p>

<p>The arrival of effective vaccines against COVID-19 has been one of the few good news stories of the pandemic. However, communicating the safety of vaccines has long been difficult, as shown by <a href="https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(20)31558-0/fulltext">most countries</a> having some level of vaccine hesitancy, including hesitancy towards <a href="https://www.imperial.ac.uk/news/216493/covid-19-vaccine-confidence-growing-global-survey/">COVID-19 vaccines specifically</a>.</p>

<p>Just as regulatory authorities – such as the European Medicines Agency (EMA) and the UK’s Medicines and Healthcare Products Regulatory Agency (MHRA) – had systems in place to assess if the vaccines worked, <a href="https://www.ema.europa.eu/en/documents/presentation/presentation-how-safety-new-covid-19-vaccines-will-be-monitored-sstraus-prac_en.pdf">so too did they create</a> carefully thought through <a href="https://www.gov.uk/government/publications/report-of-the-commission-on-human-medicines-expert-working-group-on-covid-19-vaccine-safety-surveillance">vaccine safety plans</a> to deal with any safety signals arising after the vaccines’ deployment.</p>

<p>However, this week the EU’s plan for vaccine safety was thrown into confusion. At least <a href="https://www.theguardian.com/society/2021/mar/15/which-european-states-have-paused-astrazeneca-jabs-due-to-clotting-concerns">12 EU states</a> have suspended use of the AstraZeneca COVID-19 vaccine because of concerns of a possible link between the vaccine and blood clots. These concerns are registered in spontaneous reports, where a patient or healthcare professional suspects a link between an adverse event they’ve witnessed and the vaccine. Reporters do not have to be sure of a link, and these reports do not prove there’s any association between the vaccine and the event.</p>

<p>The number of blood clots reported among people taking the vaccine, assuming even a fairly high level of under-reporting, <a href="https://www.theguardian.com/commentisfree/2021/mar/15/evidence-oxford-vaccine-blood-clots-data-causal-links">does not seem to be higher</a> than would be expected in the general population. Many things happen after vaccination that would have happened without the vaccine.</p>

<p>That said, in some countries, such as Norway and Germany, an extremely rare form of blood clot in the brain called cerebral venous sinus thrombosis (CVST) <a href="https://www.pei.de/SharedDocs/Downloads/EN/newsroom-en/hp-news/faq-temporary-suspension-astrazeneca.pdf?__blob=publicationFile&amp;v=5">has been reported</a>. Incidence of CVST in the normal population is hard to measure, although <a href="https://www.washingtonpost.com/world/2021/03/16/europe-astrazeneca-suspended-faq/">Johns Hopkins Medicine</a> has said it may affect around one in every 200,000 people each year. In Germany, the incidence of CVST post vaccination has exceeded this rate, so the EMA is carefully examining <a href="https://twitter.com/EU_Commission/status/1371810454314618889?s=20">each case</a> to look for possible contributing factors.</p>

<p>But so far, the <a href="https://www.euronews.com/2021/03/15/world-health-organization-reaffirms-safety-of-oxford-astrazeneca-covid-19-vaccine">World Health Organization</a>, <a href="https://www.bbc.co.uk/news/health-56411561">EMA</a>, <a href="https://www.gov.uk/government/news/mhra-response-to-irish-authorities-action-to-temporarily-suspend-the-astrazeneca-covid-19-vaccine">MHRA</a> and <a href="https://www.astrazeneca.com/media-centre/press-releases/2021/update-on-the-safety-of-covid-19-vaccine-astrazeneca.html">AstraZeneca</a> have all said that there is no evidence of a causal link between the vaccine and clots, and the EMA has said it is firmly convinced that the benefits of the vaccine far outweigh the risks. Yet if this is the case, why have the advisory committees of some EU states decided to suspend the vaccine?</p>

<h2 id="a-good-tool-badly-used">A good tool badly used</h2>

<p>A major reason appears to be the misapplication of the <a href="https://tinyurl.com/4yumavcf">precautionary principle</a>. This is where you take anticipatory action to avoid potential harm, even when the evidence around that harm is uncertain. It can be a useful tool when needing to make a decision in a situation that includes risk and uncertainty.</p>

<p>The precautionary principle evolved from critiques of risk assessments that were based on scientific methods. These, it was argued, were <a href="https://ajph.aphapublications.org/doi/10.2105/AJPH.91.9.1351">too conservative</a>, requiring too much evidence to prove risk, and so perhaps biased towards seeing an absence of harms.</p>

<p>The earliest forms of the principle are thought to have arisen in West Germany in the 1970s, where “Vorsorgeprinzip” was used in <a href="https://www.jstor.org/stable/30301451">environmental policy</a> to limit actions that were suspected but not proven to cause ecological damage. Past <a href="https://www.eea.europa.eu/publications/environmental_issue_report_2001_22/Issue_Report_No_22.pdf/view">case studies</a> of harms for which there were early warnings but only later actual evidence – such as asbestos – show the sorts of outcomes that the principle can potentially help avoid.</p>

<p>Regarding pausing the AstraZeneca vaccine, the principle has been cited <a href="https://www.irishtimes.com/news/health/covid-19-temporary-deferral-of-astrazeneca-vaccine-rollout-1.4509928">explicitly</a> by some EU states. Others have invoked it implicitly in interviews, saying they will “<a href="https://apnews.com/article/why-countries-stopping-astrazeneca-vaccine-shot-explained-82f4c89a76c21f287e3041b52b7a69f0">err on the side of caution</a>”. However, there are trade-offs – and that’s the primary reason why we can say the principle has been misapplied.</p>

<p>COVID-19 vaccines are being used to prevent deaths. Decisions to suspend their use will slow vaccination campaigns by reducing vaccine availability. Suspensions might also affect vaccine uptake by sparking wider concerns about safety among the public. Confidence in the AstraZeneca vaccine is already <a href="https://yougov.co.uk/topics/international/articles-reports/2021/03/07/extent-damage-astrazeneca-vaccines-perceived-safet">relatively low</a> in Europe, with high-profile comments about its effectiveness having <a href="https://theconversation.com/astrazeneca-vaccine-careless-talk-has-dented-confidence-and-uptake-in-europe-156021">dented uptake</a>.</p>

<p>So rather than avoiding risk, the principle has instead moved countries away from one risk (blood clots) towards another (lower vaccine coverage). The impact of the latter could be much larger.</p>

<p>Even if this weren’t the case, the principle has still, arguably, been misapplied. Plans for COVID-19 vaccine safety monitoring until now have been based around rigorous scientific evaluation of safety signals, careful communications to ensure vaccine hesitancy is not increased, and ensuring that signals are investigated to examine if any risk requires regulatory action.</p>

<p>Because potential safety signals arise often in vaccine and drug safety, with many being false signals, the precautionary principle <a href="https://link.springer.com/article/10.2165/00002018-200528060-00001">doesn’t fit with such plans</a>. It is too sensitive, and in the case of COVID-19 vaccines, doesn’t initiate any safety assessments that aren’t already happening.</p>

<p>As we have seen this week, misapplication of the precautionary principle leads to erratic decision making that fails to do the very thing it intends to: lower risk. The decisions made could potentially have long-term health effects both in the EU and globally. As a result, one might say we need to be more cautious about the application of the precautionary principle.</p>

<h2 id="post-publication-note">Post publication note</h2>

<p>This article was first published at <a href="https://theconversation.com/blood-clot-fears-how-misapplication-of-the-precautionary-principle-may-undermine-public-trust-in-vaccines-157168">The Conversation</a> on March 16th 2021. Since it was published the information about the risks associated with the AstraZeneca vaccine have become clearer, although the central argument of this piece still stands.</p>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[The arrival of effective vaccines against COVID-19 has been one of the few good news stories of the pandemic. However, communicating the safety of vaccines has long been difficult, as shown by most countries having some level of vaccine hesitancy, including hesitancy towards COVID-19 vaccines specifically. Just as regulatory authorities – such as the European Medicines Agency (EMA) and the UK’s Medicines and Healthcare Products Regulatory Agency (MHRA) – had systems in place to assess if the vaccines worked, so too did they create carefully thought through vaccine safety plans to deal with any safety signals arising after the vaccines’ deployment. However, this week the EU’s plan for vaccine safety was thrown into confusion. At least 12 EU states have suspended use of the AstraZeneca COVID-19 vaccine because of concerns of a possible link between the vaccine and blood clots. These concerns are registered in spontaneous reports, where a patient or healthcare professional suspects a link between an adverse event they’ve witnessed and the vaccine. Reporters do not have to be sure of a link, and these reports do not prove there’s any association between the vaccine and the event. The number of blood clots reported among people taking the vaccine, assuming even a fairly high level of under-reporting, does not seem to be higher than would be expected in the general population. Many things happen after vaccination that would have happened without the vaccine. That said, in some countries, such as Norway and Germany, an extremely rare form of blood clot in the brain called cerebral venous sinus thrombosis (CVST) has been reported. Incidence of CVST in the normal population is hard to measure, although Johns Hopkins Medicine has said it may affect around one in every 200,000 people each year. In Germany, the incidence of CVST post vaccination has exceeded this rate, so the EMA is carefully examining each case to look for possible contributing factors. But so far, the World Health Organization, EMA, MHRA and AstraZeneca have all said that there is no evidence of a causal link between the vaccine and clots, and the EMA has said it is firmly convinced that the benefits of the vaccine far outweigh the risks. Yet if this is the case, why have the advisory committees of some EU states decided to suspend the vaccine? A good tool badly used A major reason appears to be the misapplication of the precautionary principle. This is where you take anticipatory action to avoid potential harm, even when the evidence around that harm is uncertain. It can be a useful tool when needing to make a decision in a situation that includes risk and uncertainty. The precautionary principle evolved from critiques of risk assessments that were based on scientific methods. These, it was argued, were too conservative, requiring too much evidence to prove risk, and so perhaps biased towards seeing an absence of harms. The earliest forms of the principle are thought to have arisen in West Germany in the 1970s, where “Vorsorgeprinzip” was used in environmental policy to limit actions that were suspected but not proven to cause ecological damage. Past case studies of harms for which there were early warnings but only later actual evidence – such as asbestos – show the sorts of outcomes that the principle can potentially help avoid. Regarding pausing the AstraZeneca vaccine, the principle has been cited explicitly by some EU states. Others have invoked it implicitly in interviews, saying they will “err on the side of caution”. However, there are trade-offs – and that’s the primary reason why we can say the principle has been misapplied. COVID-19 vaccines are being used to prevent deaths. Decisions to suspend their use will slow vaccination campaigns by reducing vaccine availability. Suspensions might also affect vaccine uptake by sparking wider concerns about safety among the public. Confidence in the AstraZeneca vaccine is already relatively low in Europe, with high-profile comments about its effectiveness having dented uptake. So rather than avoiding risk, the principle has instead moved countries away from one risk (blood clots) towards another (lower vaccine coverage). The impact of the latter could be much larger. Even if this weren’t the case, the principle has still, arguably, been misapplied. Plans for COVID-19 vaccine safety monitoring until now have been based around rigorous scientific evaluation of safety signals, careful communications to ensure vaccine hesitancy is not increased, and ensuring that signals are investigated to examine if any risk requires regulatory action. Because potential safety signals arise often in vaccine and drug safety, with many being false signals, the precautionary principle doesn’t fit with such plans. It is too sensitive, and in the case of COVID-19 vaccines, doesn’t initiate any safety assessments that aren’t already happening. As we have seen this week, misapplication of the precautionary principle leads to erratic decision making that fails to do the very thing it intends to: lower risk. The decisions made could potentially have long-term health effects both in the EU and globally. As a result, one might say we need to be more cautious about the application of the precautionary principle. Post publication note This article was first published at The Conversation on March 16th 2021. Since it was published the information about the risks associated with the AstraZeneca vaccine have become clearer, although the central argument of this piece still stands.]]></summary></entry><entry><title type="html">Human Factors Teaching: Using storytelling.</title><link href="http://anthonycox.org/drug_safety/2021/02/13/humanfactors.html" rel="alternate" type="text/html" title="Human Factors Teaching: Using storytelling." /><published>2021-02-13T07:00:00+00:00</published><updated>2021-02-13T07:00:00+00:00</updated><id>http://anthonycox.org/drug_safety/2021/02/13/humanfactors</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2021/02/13/humanfactors.html"><![CDATA[<p><img src="/assets/birminghammedicalschool.jpeg" alt="Birmingham Medical School" /></p>

<p>A few years ago I set up a small group teaching session for pharmacy students based around a fatal adverse drug reaction, using a <a href="https://www.who.int/patientsafety/education/learning_from_error/en/">video</a> developed by the World Health Organisation. This year it is an inter-professional education event run by pharmacy and nursing academics. Sadly it will be taking place over Zoom, rather in the building you can see above, but that has made timetabling an inter-professional event easier than normal.</p>

<p>In the past I have used the event to discuss both technical and communication issues that led to the patient’s death, and for the impact the video has on first year students to raise the issues of harm in clinical practice. While revising the preparatory material, I decided to make it less technically focused, and more focused on the impact of the event and team communications. I’ve also given some limited pre-reading to enable a better understanding of the video dramatisation they are going to watch. It’s written in a less academic style than I normally use, based more around <a href="http://anthonycox.org/communication/2020/01/10/stories.html">story telling</a>. Here is the text I wrote for the teaching session, just in case it is of interest to people. For those who want an in-depth look at the case involved, you can read the <a href="https://www.who.int/patientsafety/news/Queens%20Medical%20Centre%20report%20(Toft).pdf">Toft Report</a> here in PDF format.</p>

<h2 id="just-an-ordinary-day">Just an Ordinary Day</h2>

<p>Every day thousands of healthcare professionals go to work.</p>

<p>To earn a living. To make a difference. To help people.</p>

<p>And every day healthcare professionals are involved in incidents that lead to patient harm, and in some cases deaths.</p>

<p>With very rare exceptions, none of them went to work to do this.</p>

<h2 id="here-is-a-story">Here is a story.</h2>

<p>In the 1960s, a team of scientists at Eli Lilly in the US investigated a naturally occurring chemical from the rosy periwinkle plant. The chemical was called vincristine, and they tried to use it to treat diabetes.</p>

<p><img src="/assets/elililly.jpg" alt="A press photo circa 1961 showing some members of Eli Lilly's vincristine research team" /></p>

<p><em>A press photo circa 1961 showing some members of Eli Lilly’s vincristine research team <a href="https://commons.wikimedia.org/w/index.php?curid=94448976">By Crossgates - Own work, CC BY-SA 4.0</a>.</em></p>

<p>It didn’t work.</p>

<p>But it did cause myelosuppression (suppression of the bone marrow’s ability to produce blood cells).</p>

<p>They tested it in leukaemia.</p>

<p>It worked.</p>

<p>Vincristine became a key drug in many cancer regimes. Its use in leukaemia and lymphoma has saved many lives.</p>

<h2 id="fast-forward-to-2001">Fast forward to 2001</h2>

<p>A 18 year old boy in Nottingham had successfully been treated for lymphoblastic leukaemia. He was in remission, and in the maintenance phase of his chemotherapy. This consisted of intravenous vincristine and intrathecal (into the spinal fluid) cytosine every three months.</p>

<p>Wayne Jowett had been under treatment for 2 years, but he was out of the other end. His treatment had given him a future.</p>

<p>But a terrible mistake would take all this from him.</p>

<p>On the 5th of January 2001 a doctor would inject vincristine into Wayne Jowett’s spine. The vincristine worked its way up his spine progressively paralysing him. He spent the rest of his life on paediatric intensive care, dying on the 2nd of February 2001.</p>

<p>The doctor was charged and convicted with manslaughter, but there were multiple failings at the hospital that led to this incident. This was not the mistake of one person.</p>

<p>Mistakes are rarely caused by the solely by the actions of one person. Systems of work, the way we communicate with each other, the design of equipment we use can all conspire to put those at the point of care in unsafe positions which can can harm those we seek to care for.</p>

<p><img src="/assets/waynejowett.jpg" alt="Wayne Jowett" /></p>

<p>Like <a href="http://news.bbc.co.uk/1/hi/health/3133076.stm">Wayne Jowett</a>.</p>

<h2 id="the-session">The session</h2>

<p>This session will use a World Health Organisation dramatised case similar to that of Wayne Jowett to highlight how such errors can occur. Together you will explore how the event happened, and how things could be improved to avoid such events in future. The specifics of the drugs matter less, than how the mistake arose.</p>

<p><strong>What you need to do</strong></p>

<p>During the session you will watch a video of the dramatised event. You can use this document to help you analyse the events (read it before the session).  Use a scrap of paper to jot things down to avoid using your computer.</p>

<p>You will then work as a mixed group of nursing and pharmacy students to look at the event, to find all the contributory factors that led to this event, and to look at the team working between the various professionals in dramatisation. This is a great opportunity to see different perspectives on each others professions as depicted in the video, and to learn from each other.</p>

<p>In order to protect each other, yourselves, and your patients from future errors.</p>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[A few years ago I set up a small group teaching session for pharmacy students based around a fatal adverse drug reaction, using a video developed by the World Health Organisation. This year it is an inter-professional education event run by pharmacy and nursing academics. Sadly it will be taking place over Zoom, rather in the building you can see above, but that has made timetabling an inter-professional event easier than normal. In the past I have used the event to discuss both technical and communication issues that led to the patient’s death, and for the impact the video has on first year students to raise the issues of harm in clinical practice. While revising the preparatory material, I decided to make it less technically focused, and more focused on the impact of the event and team communications. I’ve also given some limited pre-reading to enable a better understanding of the video dramatisation they are going to watch. It’s written in a less academic style than I normally use, based more around story telling. Here is the text I wrote for the teaching session, just in case it is of interest to people. For those who want an in-depth look at the case involved, you can read the Toft Report here in PDF format. Just an Ordinary Day Every day thousands of healthcare professionals go to work. To earn a living. To make a difference. To help people. And every day healthcare professionals are involved in incidents that lead to patient harm, and in some cases deaths. With very rare exceptions, none of them went to work to do this. Here is a story. In the 1960s, a team of scientists at Eli Lilly in the US investigated a naturally occurring chemical from the rosy periwinkle plant. The chemical was called vincristine, and they tried to use it to treat diabetes. A press photo circa 1961 showing some members of Eli Lilly’s vincristine research team By Crossgates - Own work, CC BY-SA 4.0. It didn’t work. But it did cause myelosuppression (suppression of the bone marrow’s ability to produce blood cells). They tested it in leukaemia. It worked. Vincristine became a key drug in many cancer regimes. Its use in leukaemia and lymphoma has saved many lives. Fast forward to 2001 A 18 year old boy in Nottingham had successfully been treated for lymphoblastic leukaemia. He was in remission, and in the maintenance phase of his chemotherapy. This consisted of intravenous vincristine and intrathecal (into the spinal fluid) cytosine every three months. Wayne Jowett had been under treatment for 2 years, but he was out of the other end. His treatment had given him a future. But a terrible mistake would take all this from him. On the 5th of January 2001 a doctor would inject vincristine into Wayne Jowett’s spine. The vincristine worked its way up his spine progressively paralysing him. He spent the rest of his life on paediatric intensive care, dying on the 2nd of February 2001. The doctor was charged and convicted with manslaughter, but there were multiple failings at the hospital that led to this incident. This was not the mistake of one person. Mistakes are rarely caused by the solely by the actions of one person. Systems of work, the way we communicate with each other, the design of equipment we use can all conspire to put those at the point of care in unsafe positions which can can harm those we seek to care for. Like Wayne Jowett. The session This session will use a World Health Organisation dramatised case similar to that of Wayne Jowett to highlight how such errors can occur. Together you will explore how the event happened, and how things could be improved to avoid such events in future. The specifics of the drugs matter less, than how the mistake arose. What you need to do During the session you will watch a video of the dramatised event. You can use this document to help you analyse the events (read it before the session).  Use a scrap of paper to jot things down to avoid using your computer. You will then work as a mixed group of nursing and pharmacy students to look at the event, to find all the contributory factors that led to this event, and to look at the team working between the various professionals in dramatisation. This is a great opportunity to see different perspectives on each others professions as depicted in the video, and to learn from each other. In order to protect each other, yourselves, and your patients from future errors.]]></summary></entry><entry><title type="html">Electronic prescribing: Different professions, similar problems.</title><link href="http://anthonycox.org/drug_safety/2020/11/09/eprescribing.html" rel="alternate" type="text/html" title="Electronic prescribing: Different professions, similar problems." /><published>2020-11-09T17:00:10+00:00</published><updated>2020-11-09T17:00:10+00:00</updated><id>http://anthonycox.org/drug_safety/2020/11/09/eprescribing</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2020/11/09/eprescribing.html"><![CDATA[<p><img src="/assets/eprescribing.png" alt="laptop" /></p>

<p>Our research group has a new paper (Open Access) looking at the experiences of multi-professional prescribers using an electronic prescribing system. We suspected some differences between the professional groups (nurses, pharmacists, and doctors), but they all reported similar experiences. The pharmacists had some differing perspectives because of their monitoring role in prescribing, but their own experiences matched those of the other professions. Not entirely unexpected given what we know about human cognitive bias.</p>

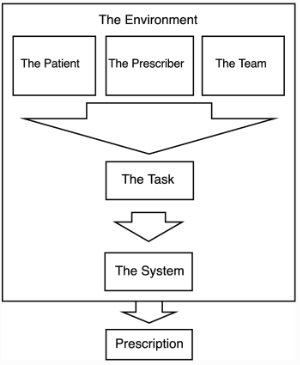
<p>We present an analysis of six major interacting themes involved in the production of a prescription. Many of these echo areas found in other studies.</p>

<p><img src="/assets/sixthemes.jpg" alt="Conceptual figure of the interaction of the six major themes leading to the production of a prescription" /></p>

<p>We conclude that:</p>

<blockquote>
  <p>Medical and non-medical prescribers have similar experience of prescribing errors when using CPOE, with the broad areas of concern aligned with existing published literature about medical prescribing. Causes of electronic prescribing errors are multifactorial in nature and prescribers describe how factors interact to create the conditions errors. Solutions focused on a single factor, such as system design or training, may only result in only limited impact on prescribing errors. While interventions should focus on direct CPOE issues, such as training and design, socio-technical and environmental aspects of practice remain important.</p>
</blockquote>

<p>Alshahrani, F., Marriott, J.F. &amp; Cox, A.R. A qualitative study of prescribing errors among multi-professional prescribers within an e-prescribing system. <em>Int J Clin Pharm</em> (2020). <a href="https://doi.org/10.1007/s11096-020-01192-0">https://doi.org/10.1007/s11096-020-01192-0</a></p>

<p>Photo by <a href="https://unsplash.com/@nci">National Cancer Institute</a></p>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[Our research group has a new paper (Open Access) looking at the experiences of multi-professional prescribers using an electronic prescribing system. We suspected some differences between the professional groups (nurses, pharmacists, and doctors), but they all reported similar experiences. The pharmacists had some differing perspectives because of their monitoring role in prescribing, but their own experiences matched those of the other professions. Not entirely unexpected given what we know about human cognitive bias. We present an analysis of six major interacting themes involved in the production of a prescription. Many of these echo areas found in other studies. We conclude that: Medical and non-medical prescribers have similar experience of prescribing errors when using CPOE, with the broad areas of concern aligned with existing published literature about medical prescribing. Causes of electronic prescribing errors are multifactorial in nature and prescribers describe how factors interact to create the conditions errors. Solutions focused on a single factor, such as system design or training, may only result in only limited impact on prescribing errors. While interventions should focus on direct CPOE issues, such as training and design, socio-technical and environmental aspects of practice remain important. Alshahrani, F., Marriott, J.F. &amp; Cox, A.R. A qualitative study of prescribing errors among multi-professional prescribers within an e-prescribing system. Int J Clin Pharm (2020). https://doi.org/10.1007/s11096-020-01192-0 Photo by National Cancer Institute]]></summary></entry><entry><title type="html">Medicines Safety Week: Special Medication Safety Edition of the International Journal of Pharmacy Practice</title><link href="http://anthonycox.org/drug_safety/2020/11/06/medsafetyspecialedition.html" rel="alternate" type="text/html" title="Medicines Safety Week: Special Medication Safety Edition of the International Journal of Pharmacy Practice" /><published>2020-11-06T08:00:10+00:00</published><updated>2020-11-06T08:00:10+00:00</updated><id>http://anthonycox.org/drug_safety/2020/11/06/medsafetyspecialedition</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2020/11/06/medsafetyspecialedition.html"><![CDATA[<p><img src="/assets/capsules.jpg" alt="Capsules" /></p>

<p>Over the past year I’ve been working on a <a href="https://onlinelibrary.wiley.com/toc/20427174/current">Special Edition</a> of the International Journal of Pharmacy Practice on focused on medication safety with some colleagues from Cardiff University. It’s been a long haul, but we have just got it out for medication safety week 2020. It has been an interesting process of filtering and reviewing papers, but I think we have an interesting mix of papers, that fit around the WHO’s global patient safety challenge.</p>

<p>We also have an <a href="https://onlinelibrary.wiley.com/doi/10.1111/ijpp.12676">editorial in the issue</a>, which gives a whistle stop tour of the papers and how they fit with the WHO framework. It concludes as follows.</p>

<blockquote>
  <p>This Safety edition illustrates the breadth and diversity of pharmacist involvement in research on patient safety from an international perspective. A recent report from the International Pharmaceutical Federation (FIP) entitled Pharmacists’ role in ‘Medication without harm’ summarises the evidence base for pharmacists’ contributions to patient and medication safety and concludes that ‘all pharmacists may consider themselves as medication safety pharmacists — advocates for safety within the healthcare system and for each individual patient’. The contributions in the Medication Safety Special Edition aim to add positively to the evidence base for medication safety, and we hope that the increasingly important role of pharmacists in medication safety and related research is demonstrated by the range of papers included from around the world.</p>
</blockquote>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[Over the past year I’ve been working on a Special Edition of the International Journal of Pharmacy Practice on focused on medication safety with some colleagues from Cardiff University. It’s been a long haul, but we have just got it out for medication safety week 2020. It has been an interesting process of filtering and reviewing papers, but I think we have an interesting mix of papers, that fit around the WHO’s global patient safety challenge. We also have an editorial in the issue, which gives a whistle stop tour of the papers and how they fit with the WHO framework. It concludes as follows. This Safety edition illustrates the breadth and diversity of pharmacist involvement in research on patient safety from an international perspective. A recent report from the International Pharmaceutical Federation (FIP) entitled Pharmacists’ role in ‘Medication without harm’ summarises the evidence base for pharmacists’ contributions to patient and medication safety and concludes that ‘all pharmacists may consider themselves as medication safety pharmacists — advocates for safety within the healthcare system and for each individual patient’. The contributions in the Medication Safety Special Edition aim to add positively to the evidence base for medication safety, and we hope that the increasingly important role of pharmacists in medication safety and related research is demonstrated by the range of papers included from around the world.]]></summary></entry><entry><title type="html">Medicines Safety Week: Finding Needles in Haystacks</title><link href="http://anthonycox.org/drug_safety/2020/11/02/medsafetyweek2020.html" rel="alternate" type="text/html" title="Medicines Safety Week: Finding Needles in Haystacks" /><published>2020-11-02T08:00:10+00:00</published><updated>2020-11-02T08:00:10+00:00</updated><id>http://anthonycox.org/drug_safety/2020/11/02/medsafetyweek2020</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2020/11/02/medsafetyweek2020.html"><![CDATA[<p><img src="/assets/needleinahaystack.jpg" alt="Needle in a haystack" /></p>

<p>It’s Medicines Safety week. The twitter hashtag <a href="https://twitter.com/search?q=%23MedSafetyweek">#medsafetyweek</a> shows a lot of international activity to encourage awareness of the harms of medicines, with a special emphasis on the importance of everybody playing their part in reporting suspected side effects of medicines. Every report counts.</p>

<p>The MHRA’s Yellow Card Scheme has been established since 1964 and has just reached the milestone of having a million reports submitted. When you make a single report, you might think it won’t have great impact, but it can. The MHRA as part of today’s celebrations have highlighted the case of <a href="https://www.gov.uk/government/news/milestone-1-million-yellow-card-report-for-suspected-side-effects-in-medsafetyweek">a single patient reporting</a>, leading to a change in medicine information. I think this sort of <a href="http://www.anthonycox.org/communication/2020/01/10/stories.html">story telling about the reporting of side effects</a> is so important to encourage further reporting. It’s great to see the MHRA doing this.</p>

<p>However, it isn’t the only story. You might think once an individual report of a suspected side effect has been analysed, it just disappears into the haystack of reports where we are looking for those valuable needles. However, because of the way in which we find side effects in databases such as the Yellow Card Scheme, through signals of <a href="https://link.springer.com/article/10.1007/s40264-020-00911-w">disproportionality</a>, every existing card also helps find side effects from new reports that are submitted.</p>

<blockquote>
  <p>Disproportionality analysis is primarily a tool to generate hypotheses on possible causal relations between drugs and adverse effects, to be followed up by clinical assessment of the underlying individual case reports. It is based on the contrast between observed and expected numbers of reports, for any given combination of drug and adverse event.</p>
</blockquote>

<p>Unlike trying to find a needle in a haystack, where the haystack is in the way, finding an adverse effect in a database requires the haystack of previously submitted reports to find a possible link between a drug and a side effect.</p>

<p>Those million reports continue to serve a purpose.</p>

<p>Every report counts. Twice.</p>

<p>Photograph: Photo by <a href="https://unsplash.com/@idellamaeland">Idella Maeland</a></p>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[It’s Medicines Safety week. The twitter hashtag #medsafetyweek shows a lot of international activity to encourage awareness of the harms of medicines, with a special emphasis on the importance of everybody playing their part in reporting suspected side effects of medicines. Every report counts. The MHRA’s Yellow Card Scheme has been established since 1964 and has just reached the milestone of having a million reports submitted. When you make a single report, you might think it won’t have great impact, but it can. The MHRA as part of today’s celebrations have highlighted the case of a single patient reporting, leading to a change in medicine information. I think this sort of story telling about the reporting of side effects is so important to encourage further reporting. It’s great to see the MHRA doing this. However, it isn’t the only story. You might think once an individual report of a suspected side effect has been analysed, it just disappears into the haystack of reports where we are looking for those valuable needles. However, because of the way in which we find side effects in databases such as the Yellow Card Scheme, through signals of disproportionality, every existing card also helps find side effects from new reports that are submitted. Disproportionality analysis is primarily a tool to generate hypotheses on possible causal relations between drugs and adverse effects, to be followed up by clinical assessment of the underlying individual case reports. It is based on the contrast between observed and expected numbers of reports, for any given combination of drug and adverse event. Unlike trying to find a needle in a haystack, where the haystack is in the way, finding an adverse effect in a database requires the haystack of previously submitted reports to find a possible link between a drug and a side effect. Those million reports continue to serve a purpose. Every report counts. Twice. Photograph: Photo by Idella Maeland]]></summary></entry><entry><title type="html">World Patient Safety Day</title><link href="http://anthonycox.org/drug_safety/2020/09/17/worldpatientsafetyday2020.html" rel="alternate" type="text/html" title="World Patient Safety Day" /><published>2020-09-17T09:00:10+01:00</published><updated>2020-09-17T09:00:10+01:00</updated><id>http://anthonycox.org/drug_safety/2020/09/17/worldpatientsafetyday2020</id><content type="html" xml:base="http://anthonycox.org/drug_safety/2020/09/17/worldpatientsafetyday2020.html"><![CDATA[<p><img src="/assets/jamesyarema.jpg" alt="Tablets" /></p>

<p>It’s patient safety day. If you go to twitter and look at the hashtag <a href="https://twitter.com/search?q=%23WorldPatientSafetyDay">#WorldPatientSafetyDay</a> there’s lots of interesting and valuable material that can be used to make healthcare a safer place for both patients and healthcare staff.</p>

<p>But there is one easy small thing you can do to have huge impact.</p>

<p>This year make a commitment to spend 5 minutes on one thing that adds to global patient safety.</p>

<p>You can definitely do it if you are a health professional.</p>

<p>You might be able to do it if you are a patient or a carer, but I hope you don’t need to.</p>

<p>You can report a suspected adverse reaction (side effect) to your country’s regulatory system.</p>

<p>We don’t know much about the real-world safety of new drugs and vaccines when they first come to market. We can predict what might happen from the studies that got the drug or vaccine licensed, but when they are used in the wider population new side effects might become apparent. Sometimes even mild side effects may be indicative of a more serious issue in other patients.</p>

<p>Therefore every report of suspected adverse drug reactions that regulators receives adds a little knowledge. That knowledge accumulates. And over time that aggregation of data can give a signal of possible harm. And that helps regulators keep us all safe by focusing where they need to look.</p>

<p>So if you take a medicine or a vaccine this year, please let regulators know if you suffer a side effect.</p>

<p>You probably won’t.</p>

<p>You might even think the side effect is from something else. But you only have to suspect, not be sure. And each one helps other patients by ensuring we know a drug or vaccine is safe, or alternatively allowing us to find a problem that can be prevented in others.</p>

<p>If you are a health professional, just reporting one of the many suspected adverse drug reactions you see a year will make you better than average reporter.</p>

<p>And it will take you 5 minutes.</p>

<p>Once a year.</p>

<p>Photograph: Photo by <a href="https://unsplash.com/s/photos/medicine?utm_source=unsplash&amp;utm_medium=referral&amp;utm_content=creditCopyText">James Yarema</a></p>]]></content><author><name></name></author><category term="drug_safety" /><summary type="html"><![CDATA[It’s patient safety day. If you go to twitter and look at the hashtag #WorldPatientSafetyDay there’s lots of interesting and valuable material that can be used to make healthcare a safer place for both patients and healthcare staff. But there is one easy small thing you can do to have huge impact. This year make a commitment to spend 5 minutes on one thing that adds to global patient safety. You can definitely do it if you are a health professional. You might be able to do it if you are a patient or a carer, but I hope you don’t need to. You can report a suspected adverse reaction (side effect) to your country’s regulatory system. We don’t know much about the real-world safety of new drugs and vaccines when they first come to market. We can predict what might happen from the studies that got the drug or vaccine licensed, but when they are used in the wider population new side effects might become apparent. Sometimes even mild side effects may be indicative of a more serious issue in other patients. Therefore every report of suspected adverse drug reactions that regulators receives adds a little knowledge. That knowledge accumulates. And over time that aggregation of data can give a signal of possible harm. And that helps regulators keep us all safe by focusing where they need to look. So if you take a medicine or a vaccine this year, please let regulators know if you suffer a side effect. You probably won’t. You might even think the side effect is from something else. But you only have to suspect, not be sure. And each one helps other patients by ensuring we know a drug or vaccine is safe, or alternatively allowing us to find a problem that can be prevented in others. If you are a health professional, just reporting one of the many suspected adverse drug reactions you see a year will make you better than average reporter. And it will take you 5 minutes. Once a year. Photograph: Photo by James Yarema]]></summary></entry></feed>